Alaska HIPAA Authorization
What this document covers
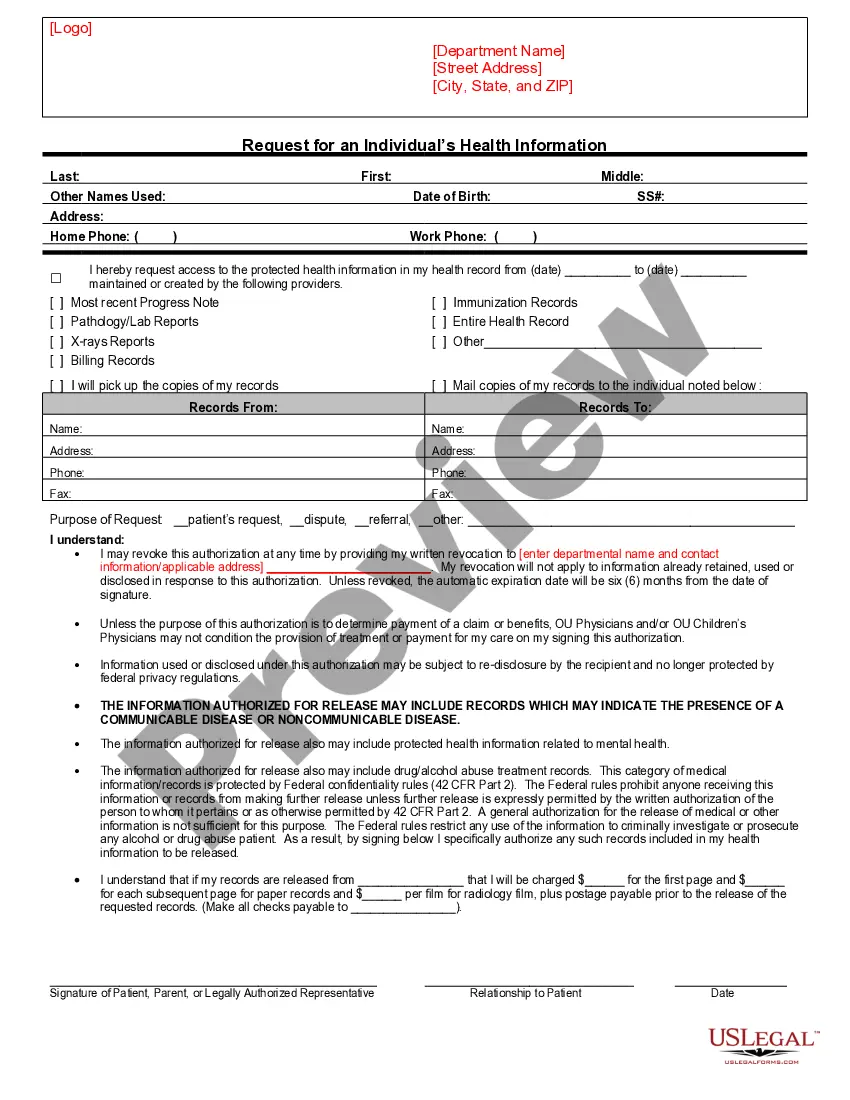
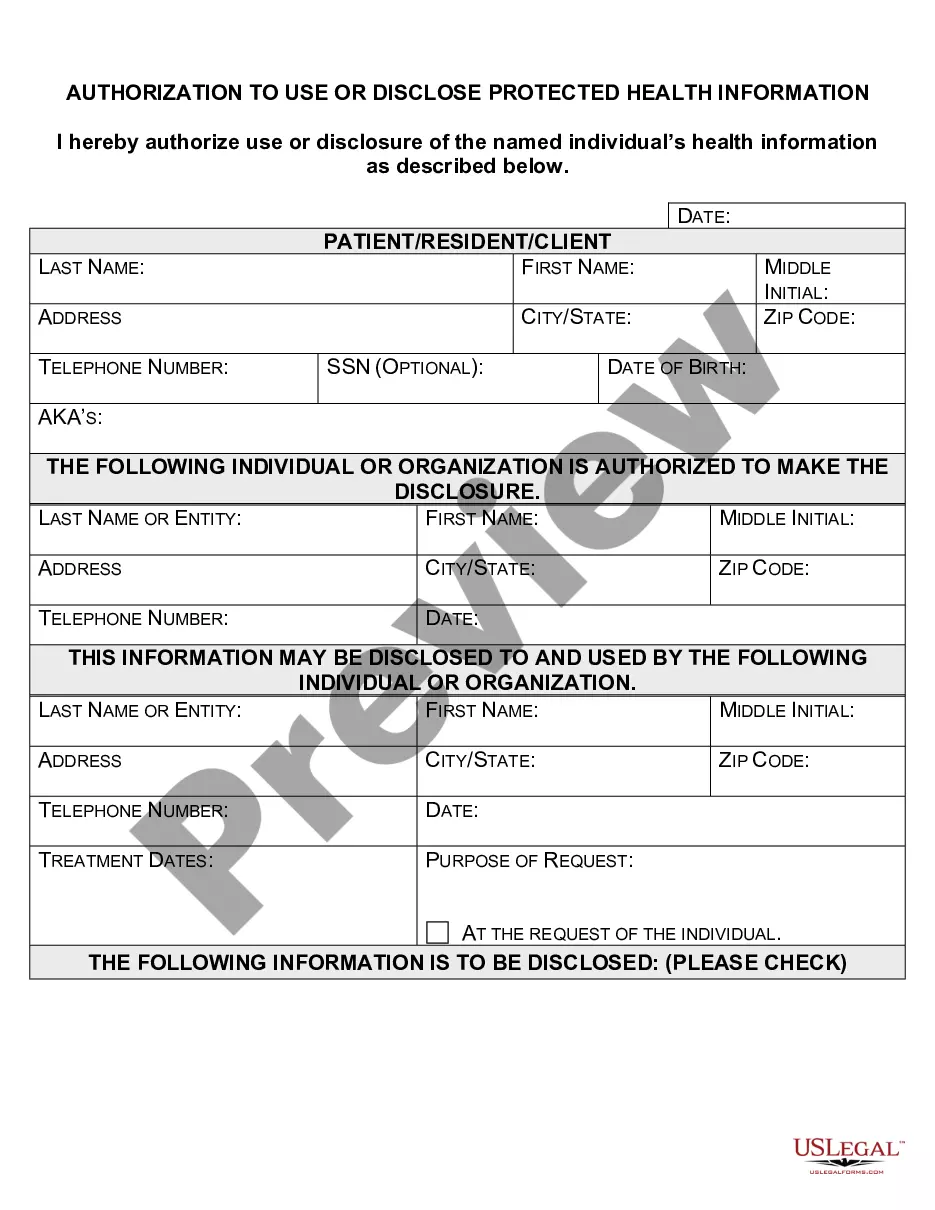
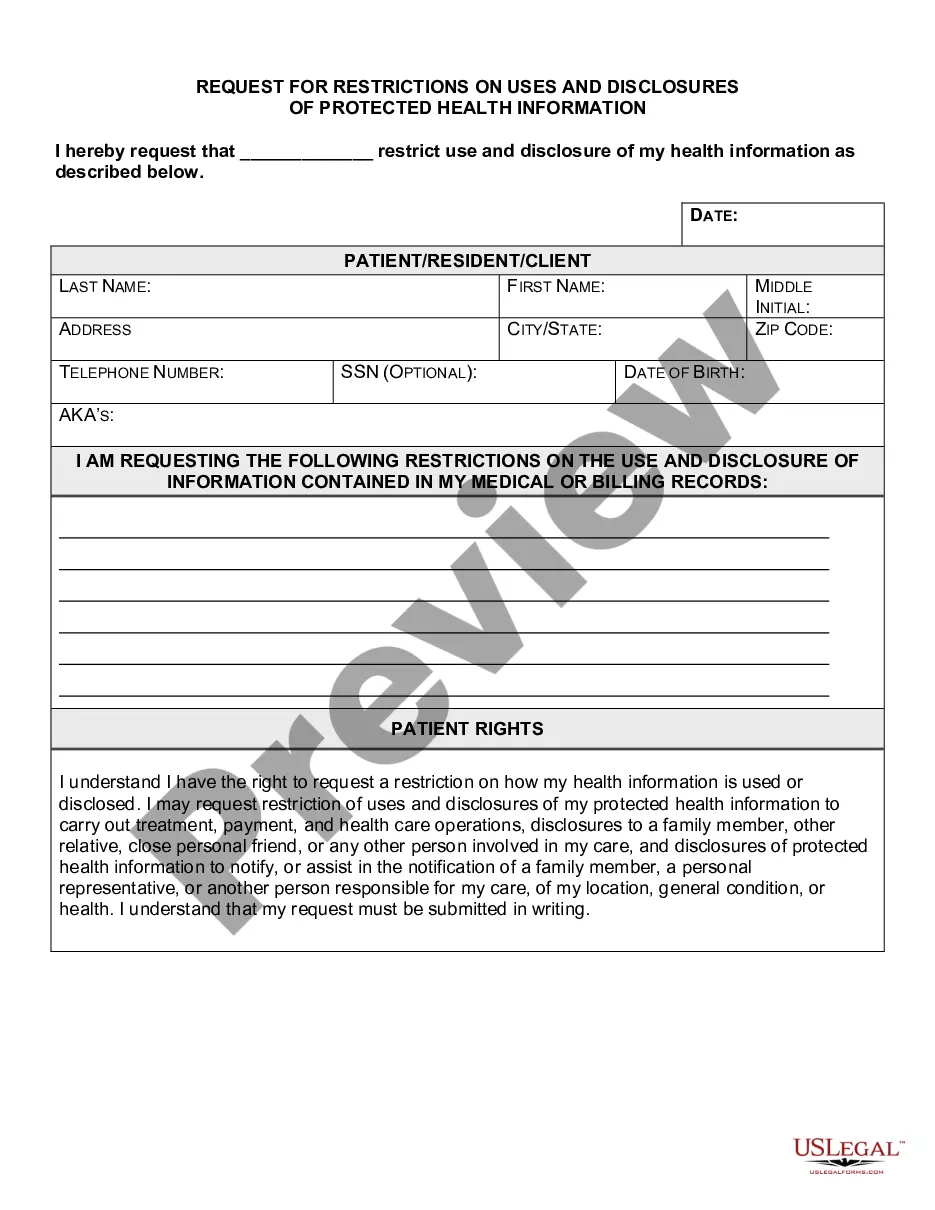
The Alaska HIPAA Authorization is a legal form that allows individuals to authorize the use or disclosure of their protected health information by their healthcare providers. This authorization is required under the Health Insurance Portability and Accountability Act (HIPAA), ensuring that personal health information can be shared securely for treatment and other purposes. Unlike general health information releases, this form is specifically tailored to meet the requirements of Alaska law and the unique privacy protections associated with it.
What’s included in this form
- Authorizes a specific healthcare provider to use or disclose health information.
- Defines the effective period of the authorization, covering all past, present, and future healthcare periods.
- Specifies the extent of the information being authorized for release, including the complete health record.
- Clarifies the purposes for which the information may be used, such as medical treatment, billing, or claims payment.
- Details the termination of the authorization, stating it remains valid until the death of the patient.
- Includes patient identification fields, such as name, address, and date of birth.




Situations where this form applies
This form should be used when a patient wants to allow healthcare providers to share their protected health information with another person or entity. This could be necessary for situations such as coordinating treatment with specialists, handling insurance claims, or providing information to family members involved in the patient's care.
Who this form is for
- Patients who wish to authorize their healthcare providers to share their medical information.
- Individuals looking to facilitate communication between different healthcare providers involved in their care.
- Patients needing to allow family members or other individuals access to their health records for treatment or decision-making purposes.
Steps to complete this form
- Identify your healthcare provider by filling in their name, title, facility, and contact information.
- Specify the individual authorized to receive your health information.
- Fill in your personal information, including your name, address, and date of birth.
- Sign and date the authorization to validate your consent.
- Keep a copy of the signed form for your records.
Notarization requirements for this form
This form does not typically require notarization unless specified by local law. However, it is always advisable to check local regulations for any specific requirements.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Mistakes to watch out for
- Failing to include complete and accurate contact information for the healthcare provider.
- Not specifying the individual or entities authorized to access health information.
- Leaving out necessary patient demographic information, which may delay processing.
Why use this form online
- Easy to download and print, allowing for quick access whenever needed.
- Editable format helps in filling in necessary details accurately.
- Secure storage of the completed form ensures confidentiality of health information.








